

From the September 2nd NEJM:
You are a primary care physician at a community health center. A 60-year-old man without any known chronic medical conditions comes to you for a routine visit, accompanied by his wife. You obtain a history. He is up to date on age-appropriate cancer screenings and immunizations. He last saw a primary care physician several years ago. The patient states that he feels well overall and does not have any new medical concerns. He takes famotidine for occasional gastroesophageal reflex disease and trazodone to help him sleep. There have been no recent medication changes. He works as an architect and lives with his wife of 20 years, who encouraged him to reengage with a primary care physician. The patient drinks two or three alcoholic beverages a week and does not smoke.
In the clinic today, his blood pressure is 126/88 mm Hg, heart rate is 72 beats per minute, and oxygen saturation is 98% while he is breathing ambient air. You decide to pursue a laboratory workup that includes a complete blood count, comprehensive metabolic panel, lipid profile, measurement of the glycated hemoglobin level, and thyroid-function tests.
The patient is otherwise healthy and asymptomatic. You must decide whether you should perform a routine physical examination during the visit or whether a physical examination is not necessary.
I was asked to write a response to this case, tasked with arguing against performing a routine physical exam. I was happy to draw this side of the argument as it aligns with my actual thinking.
That said, I do what I consider performative physical examinations on healthy people who are in for a “checkup”. I listen to a patient’s heart and lungs and check three pulses (the right radial and both dorsales pedis). I also occasionally do other parts of the exam, maybe if I am looking for something to demonstrate to a student.
I do this exam because I think the patient expects it or because it feels like a good transition to the end of the visit. If I were truly to walk the walk, I would tell my patient the visit is over, ask whether they were expecting an exam, and, if they said yes, explain why I wasn’t doing one.
Do give the NEJM article a read. I think this is an interesting debate, and I was flattered to be paired with Dr. Goroll, a real giant in my field. For all their benefits, medical journal websites are not great for hosting discussions. So, after reading the article – really, after reading the article -- please comment below. I leave the comments open to all.
Read this next part only if you have nothing else to do and you want to listen to me vent about X/Twitter.
I know, you’re probably thinking, social media is awful; what kind of a child are you, Adam, that you are only just realizing this! I have a complicated relationship with social media. I recognize that it can be a cesspool, but I also get quite a bit out of it. The give-and-take can be interesting, and the ability to self-publish has given me an outlet later in my career.
I delayed this Substack post for a couple of weeks after the NEJM article was published because I found the Twitter discussion that followed its publication both exhausting and depressing. Many people who commented apparently did not read the article – some brave souls admitted as much. Many chose to assume that I was arguing against performing a physical examination ever. Others responded by noting the time that they did an exam and found something – seemingly oblivious to the fact that the hundreds of times they did the exam without finding anything might have done harm or that detecting an asymptomatic finding at time X does not guarantee a better outcome than waiting for symptoms at time Y. (I do have a really nice lecture on lead time, length time, and overdiagnosis bias if anyone is interested…).
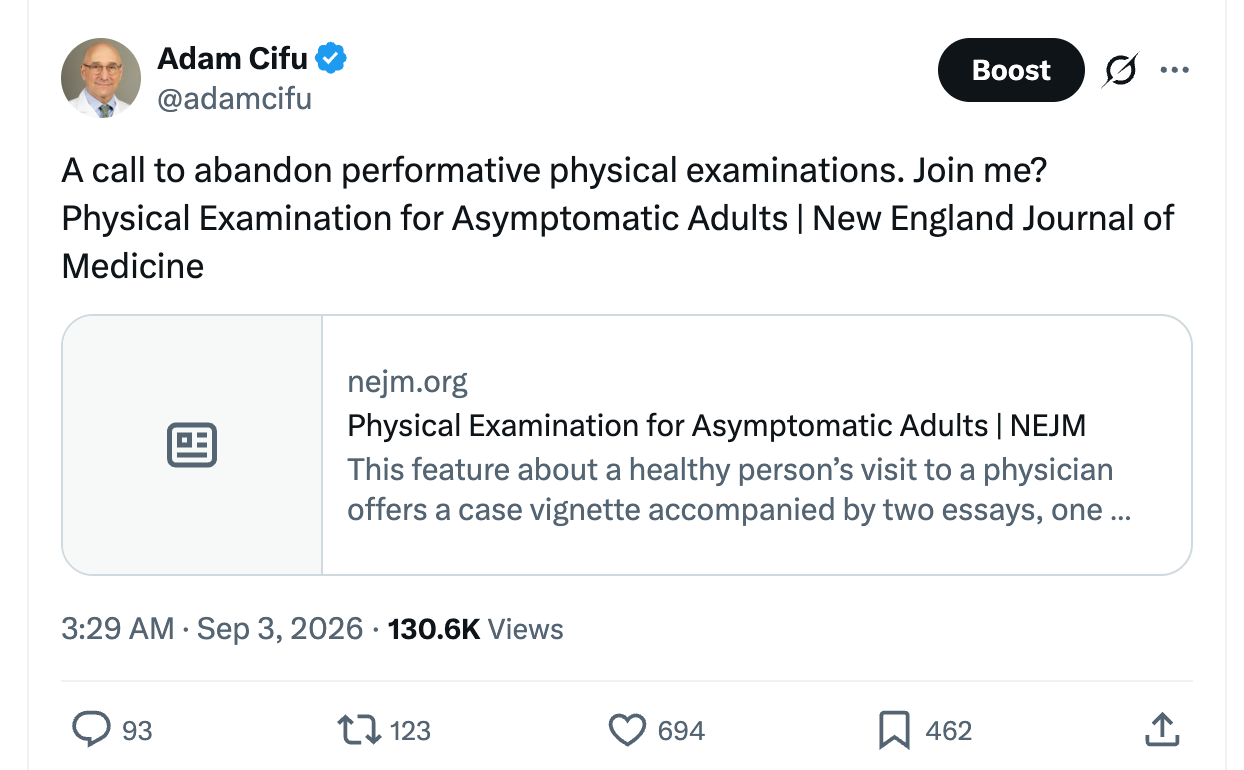
The response was partially my fault; here is my tweet:
I could have provided a more balanced intro like:
A debate about the ROUTINE physical examination, hosted by the NEJM, in which I was assigned to argue against it.
But, come on, look at those numbers: 130,000 views? 😉
NEJM probably deserves some of the blame too, since the article was paywalled, so I am sure some people who had to comment couldn't read it.
I have to remind myself that the internet is not a place for thoughtful academic debate, where we can agreeably disagree and occasionally try out opinions we are not totally committed to. I am thankful that Sensible Medicine often provides such a space.
OK, I feel better now.
Photo from the CDC on Unsplash
I've been a very busy FM doc for over 31 years, and have seen the transition from full physicals including pelvic/rectal/etc yearly to "periodic check ups" the recommended timing of which I base on patient sex/age/comorbidities/etc. I have become a huge proponent of NOT doing much physical exam, based on the data and lack of evidence to support it, and arguably the time spent in directed discussion with a patient bears far more fruit than a routine exam when asymptomatic.
However...
There have been 2 incidents that have helped me modify/adapt the all or none approach. One was early in the career when I saw a patient for a routine check up, their only medical history was longstanding hypothyroidism, stable on levothyroxine and their labs once again confirmed well controlled TSH and no symptoms. I refilled the rx and said I'd see them again in a year. That patient lodged a complaint with the medical director about how I "didn't even examine her", so how could I have been so sure things were ok? In reviewing the complaint with me, the older and wiser clinician told me that though I wasn't actually wrong in my approach, and I can have all the salient evidence in the world with which to reassure a patient, it's the "laying on of hands" that makes them feel evaluated and cared for.
The second was much more recent, earlier this year. I was seeing a new patient with well controlled hypertension and hyperlipidemia, who wished to get some support with lifestyle change and weight loss. He reported being very active at work, enjoyed dancing 2-3 times a week, cycles regularly, and aside from some skin concerns that I addressed, really didn't have much else going on. As I was wrapping up the hour long visit (DPC rocks!), he asked if we were done, since I hadn't really examined him. I launched in to my explanation as to why we were moving away from a routine "full physical" for all the reasons elucided by Dr. Cifu in the NEJM article, but I had him get on the table and did my regular "make them feel good" exam. Well hot damn if he didn't have an irreg irreg rhythm, confirmed as a. fib on ECG. Huh. After that finding, and additional questioning, it turned out that well yes, he DID have more exertional dyspnea lately, and couldn't dance as vigorously as he may have a year ago without slowing to rest. He had chalked it up to weight so didn't mention it.
Now one could argue that I didn't really need to diagnose this, his CHADS-VASC and HAS-BLED scores were both 1, he is uninsured/not flush with cash, and my recommended cardiac work up and even the discussion of Eliquis vs coumadin(and the lab testing it entails) and their costs gave him pause. He opted for no anticoagulation, and we are seeing each other regularly for the lifestyle change support, HR evaluations, etc. Last visit he informed me that he knows he won't live forever and the risk of stroke is acceptable to him. That's a whole other discussion we could have here I guess - clot vs bleed risks and why we overwhelmingly prefer to expose patients to dangerous bleeding over risking the clot? But I digress.
Suffice it to say we will overdiagnose if we do too much examination in asymptomatic people, and we will absolutely miss some pathology by avoiding it. As with everything in this complex, maddening profession, you make the best educated decision based on the data, tempered by the patient in front of you, and hopefully most of the time the partnership of intellect/intuition will serve you well.
I have given this a lot of thought over my 35 year career. I am a retired emergency doc. I did not have to deal with this much as a routine physical was not part of my responsibilities. Currently, however, I am an Aviation Medical Examiner which means that I perform regulatory medical exams for pilots and aspiring pilots. Much of the testing is geared toward visual acuity and color vision deficiency. Blood pressure, pulse, height and weight are routinely performed. The exam is meant to detect conditions that can cause sudden or subtle incapacitation. Imagine my surprise when I first started my training for this role that anus and genital exams were on the list of things that I was supposed to perform. The only check boxes available for each exam item were "normal" and "abnormal". Sensibly, in the last year, the FAA has added a box for "not performed" (which, in all likelihood, is what "normal" meant for most docs doing these exams...at least I hope so for the sake of unsuspecting pilots). I haven't gotten an adequate explanation as to why these were on the list in the first place but I did receive some insight from a pilot with whom I spoke who had a rectal exam during one of these appointments. The examining physician, when asked why this needed to be done, responded with "what if you have a hemorrhoid?". I had no words. As for the genital exam I can only speculate on the conditions that might cause incapacitation. What if the pilot has balanitis! I am required to examine the applicant from head to toe and report on 24 different elements (minus the 2 above). I do perform all of these because that's my job and I am required to attest to each of these elements. However, this has led me to ponder which of these exam items is likely to uncover a potentially incapacitating condition. I am guessing that "the money" is on the cardiovascular exam (Aside from auscultation of the heart I listen for bruits and palpate for the abdominal aorta). The remainder of the exam, however, seems mostly irrelevant to safety of flight. Sure, there are cases where physical limitations of strength or range of motion may be relevant to the ability to operate an aircraft but most of those would be obvious on a cursory exam. I apologize that this is a bit tangential to the topic at hand but it has been on my mind. As a final note, most of my physician friends have related their skepticism regarding the utility of routine complete exams.