

Reading Sensible Medicine can make you feel like medicine is broken. We argue that medicine is full of excess, pharma-corrupted research, and a lack of common sense. While that is true, medicine still has much to be proud of. Every day, I am impressed by my colleagues' commitment and smarts. The progress in areas ranging from cystic fibrosis to amyloid cardiomyopathy to malignant melanoma over the last decade has been breathtaking.
I’ve written a few shameless promotional pieces for Primary Care/General Internal Medicine. Here is another one. My daughter recently told me that I write a lot ot listicles, so here is another one: seven things I love about being a general internist
Getting paid to answer people’s questions and work toward making them better
This realization inspired this post. Some mornings and afternoons, I don’t have patients scheduled. These hours are supposed to be filled with writing, lecture preparation, administrative responsibilities, and tasks left over from clinic sessions. In truth, what often occupies this time is answering calls, texts, emails, and MyChart messages from people who need help managing their health. I find it amazing that I get paid to basically be a 311 line for my patients. I struggle to imagine a more satisfying and rewarding way to spend a day.
Puzzling through medical mysteries
I’d be lying if I said the majority, or even a large minority, of my clinical time goes to solving Holmesian (Housian?) level mysteries. Much of what I do is routine, completing diagnostic or therapeutic tasks that I’ve done a thousand times before: evaluating dysphagia, treating a UTI, adjusting insulin dosing, and the like.
But, a few times a week, people come in with symptoms whose etiology is not obvious. I love the puzzle of trying to make a diagnosis parsimoniously, causing the patient the least trouble and spending the fewest healthcare dollars.
Trying, and failing, to master medicine
I’ve written this many times in many different ways. There may be a finite number of diseases, but with over eight billion people, the possible presentations are essentially infinite.
Every day, I get to read articles about diseases and treatments, not just because they are interesting or so I’ll have more to say at a cocktail party, but to actually help people. I’ll see a patient with an interesting problem, and I’ll have to dive into the medical literature, broadly defined, to solve it.
Although I deeply love this challenge, when I occasionally, invariably, get things wrong, the last thing I am thinking is, “Isn’t it great that medicine is so hard!”
Building and maintaining relationships
I’ve been in the same practice in the neighborhood where I live and where my kids went to school for 29 years. It's been an absolute pleasure to watch my patients change and our relationships develop. I have patients I started seeing when they were in their teens who are now in their 40s. My feelings for some of these people are best described as paternal.
It has been delightful watching a web of patients’ families and friends become my patients. It once made me uncomfortable, but I now enjoy socializing with my patients at work, at school functions, around the neighborhood, and even at my own colonoscopy.
I feel ridiculously fortunate that my work has introduced me to people I would never have otherwise met. I am sure that these relationships have made me a better person.
Working with colleagues
My clinical colleagues are a total joy. These are smart, accomplished people from whom I constantly learn. These are people who derive the same pleasure from caring for people as I do. There is never a week that I don’t walk away from a conversation with a colleague impressed.
I get that there are a whole lot of problems with social media. I won’t even list a handful of them, for fear of excluding important ones. Acknowledging that, through Twitter, X, and now Substack, my circle of colleagues has grown exponentially. It is a pleasure to interact with people from, quite literally, around the world, about patient care issues, academic pursuits, and even homemade ice cream sandwiches. These relationships have led me to visits near and far. I thought I’d come back from these trips with another line on my CV, a bit of ego boost, and — occasionally — a small honorarium. In fact, I come back enriched with new ideas, renewed enthusiasm for my work, new colleagues, and sometimes new friends.
Caring for everything (with backup)
As a resident, I’d complain when surgery declined to admit a patient with cholecystitis or a partial SBO. I’d whine when neurology passed on a patient with a completed stroke. I’d seethe when anyone pregnant ended up on my service. Although none of these patients needed surgical, neurologic, or obstetrical care, they weren't well enough to go home. So, they ended up on medicine. Medicine can never refuse a patient.
Then I grew up. I realized that the beauty of the field in general, and of my specialty in particular, is that we care for anything and everything. I’ll happily manage your heart failure, your thyroiditis, and your pneumonia. I’ll also think hard about when my patients would do better (or worse) seeing a subspecialist.
Being a good general internist means knowing what every specialist can and will offer. It means knowing enough about everything that you know what you don’t know enough.
The money is good
Talking about money is generally considered unseemly. But we hear about people choosing ortho, or ophtho, or derm for the money, so it’s probably worth acknowledging. I am more than satisfied with the money I make. In fact, I can’t believe I am paid so well to do something I love so much. I certainly don’t make master-of-the-universe money. (Nobody in medicine does, and I chuckle at those who think they do.) I don’t deserve that kind of wealth. I’ve taken no risks; I just chose a path, worked hard, and got lucky.
Here is some recent data about physician income.
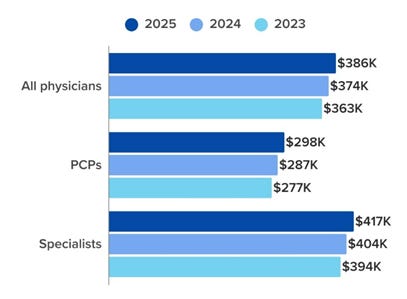
Even for a single-earner family, this puts a PCP in the top 10% of yearly incomes for Americans. Given that 20% of doctors are married to other doctors, those people are comfortably in the top 1%.
Ok, there are caveats. Most doctors don’t start earning real money until their early 30s. That’s 10 years of income to make up if you compare yourself to a peer who got a well-paying job right out of college. It is also true that many students graduate with quite a bit of debt. (Though it is also true that a large proportion of medical students come from families of means who pay their way. Take a look at this terrific study by previous Sensible Medicine contributor @armanshahriar.)
Considering how good the job is, to be compensated handsomely is pretty great. You’ll never get rich as a primary care general internist, but if you live within your means, you’ll be fine.
I do love what you have highlighted. It gets even better when, as physicians, we are resolving some of the chronic diseases rather than managing and chasing them. I enjoyed being an internist, but I truly love practicing functional medicine, which engages the patient in their own care.
“I don’t deserve those kinds of riches. I’ve taken no risks; I just chose a path, worked hard, and got lucky.”
I’m going to add, “I’ve loved GOD, and loved people.”
Good article my friend. Thank you.