

The question is stroke prevention in patients with atrial fibrillation (AF) who have only one stroke risk factor. Risk factors include age > 65, high blood pressure, diabetes, vascular disease and heart failure. Of course, these are the anointed risk factors because they were part of the CHADSVASC score. Other risk factors that may influence stroke risk are atrial size and function as well as duration of AF.
For the sake of argument I will stay with the traditional risk factors.
Current guidelines (experts) say we should give these patients oral anticoagulation (OAC) because [they think] the yearly stroke risk is around 1-2% per year. OAC reduces stroke risk by about 60%. But it also may increase bleeding.
But all this is based on old data from the warfarin trials 20-30 years ago. Things have changed. AF is much easier to diagnose and we can now find 1 hour of AF with a smartwatch.
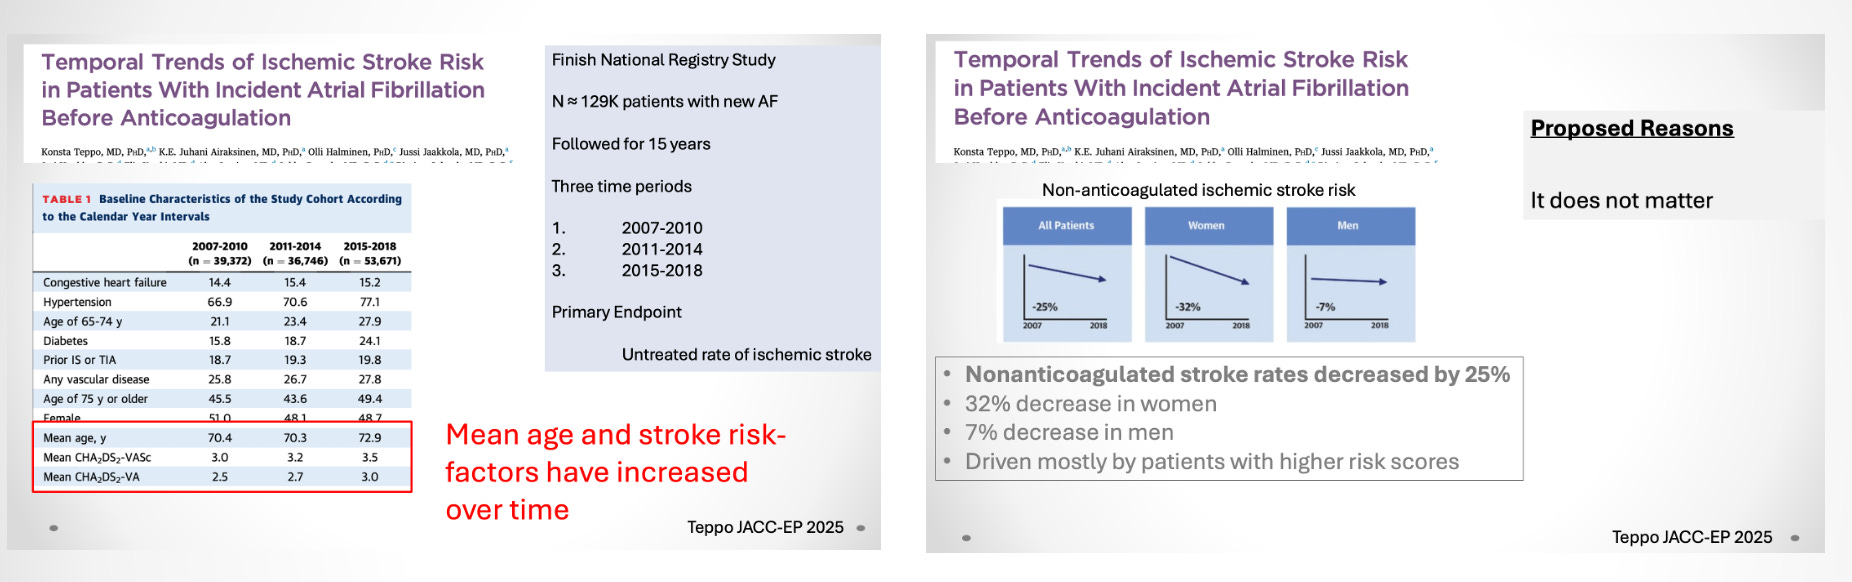
Observational studies have found a declining incidence of stroke in patients with AF—even though the risk factors are increasing. Something about 2026 AF is less risky than AF in the 1990s.
One more thing before I tell you about the SINGLE AF trial. It’s not nothing to give a 55-year-old patient a diagnosis of AF and treat them with a daily anticoagulant. That’s a lot of tablets over the decades.

SINGLE AF Trial
South Korean teams randomized 1800 patients with AF and one risk factor to a direct acting oral anticoagulant (DOAC) or no DOAC. They then measured a primary outcome of stroke, systemic embolism, major bleeding or cardiovascular death.
These were 60-year-old patients, 75% male and about two-thirds had intermittent AF while one-third had persistent AF.
Here are the KM curves:
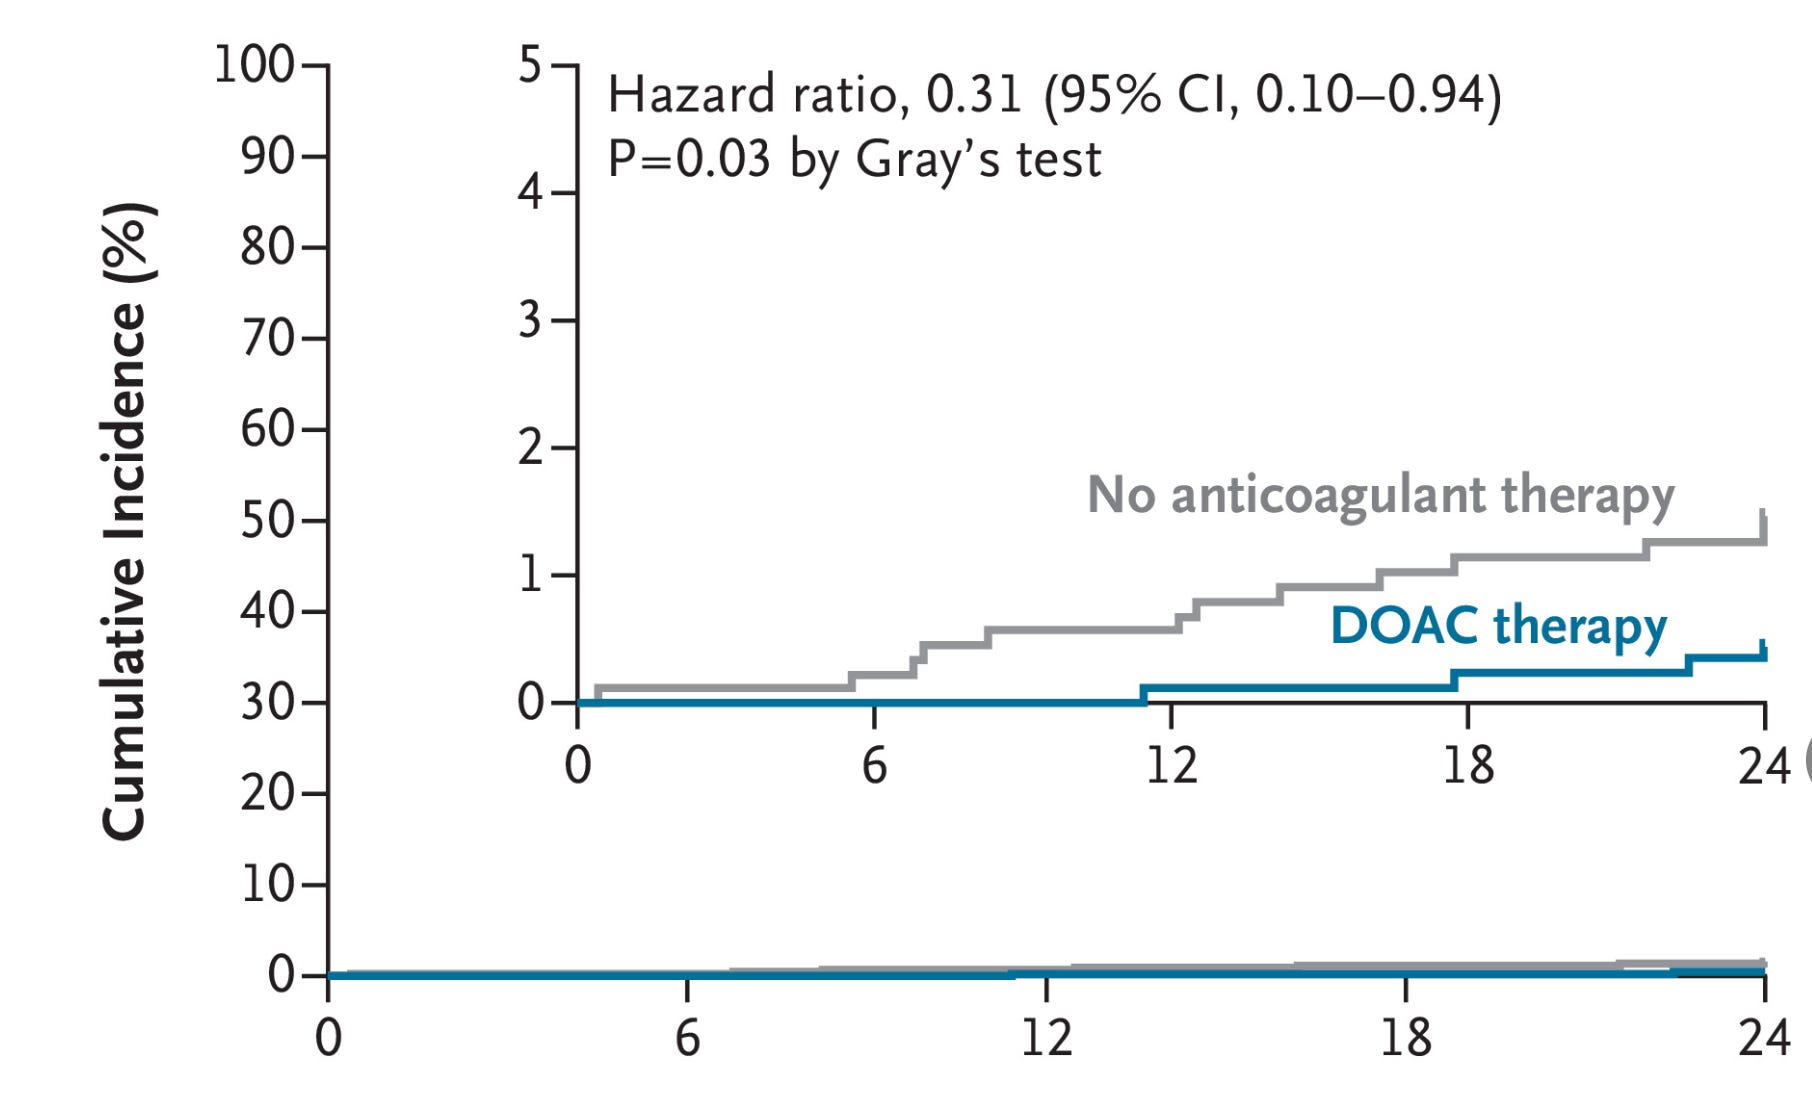
Notice the y-axis insert. After approximately 2 years of follow-up, a primary endpoint occurred in 4 of 901 patients (0.5%) in the DOAC arm vs 13 of 902 patients (1.5%) in the no DOAC arm. The absolute risk difference was -1.0% (95% CI, -2.0 to -0.1; P = .03).
Stroke events were even lower. Three vs ten strokes in the DOAC vs no-DOAC arm respectively. Major bleeding was even lower yet (3 vs 4) patients.
The yearly stroke risks were 0.55% in the control arm vs 0.15% in the DOAC arm. I also went into the supplement and learned that 7 of the 10 strokes in the control arm were modified Rankin score 0 or 1, which translates to either no or minor deficits.
Comments and Lessons
When assessing trials we ask whether the effect size is clinically meaningful and statistically robust.
Effect size: Times have changed with AF. It’s just not as risky as it used to be. In SINGLE AF, which had many patients with persistent AF, the stroke rate with no OAC was only 0.55% per year. While it was lower with DOAC, the reduction was small at 0.4% per year. That means you have to treat 250 patients with daily OAC to prevent one stroke. And 70% of the strokes were very mild.
When I wrote about this in Munich where it was presented at the ESC congress, I felt that if you did nothing, very little bad happened and if you did something (gave DOAC), very little harm came. The tiny effect size stems from a super low base rate of stroke when only one risk factor is present.
Statistical Fragility: You hardly need a calculator to posit that 3 vs 10 strokes in 1800 patients could occur by chance. A formal calculation of the fragility index is 2, meaning if 2 events occurred in the other group, statistical significance would be lost. This complicates matters because it’s possible that the absolute risk reduction is noise rather than true effect.
Translation is Hard
Another thing we do when assessing trials is ask about external validity. That is…how can we apply this to people we see in our clinic.
Modernity has complicated SINGLE AF trial translation. Let’s say a person has 2-hour episodes of AF on a smartwatch. We call this subclinical AF. The ECG rhythm is still AF, but it is unlike the AF that used to occur in the past. A patient in the year 2005 had to feel palpitations, then make an appointment at a doctor’s office and then get an ECG. IOW…they had to be in AF a lot longer than 1-2 hours.
We know from the NOAH and ARTESIA trials that oral anticoagulation has little to no net benefit in patients with short-duration AF. These were much higher stroke risk patients (CHADSVASC ≈ 4) but had yearly stroke rates of approximately 1%. DOAC reduced the risk of stroke a little but increased bleeding by as much.
So…if short duration AF is this low-risk, imagine a patient with only one risk factor. It’s going to be even lower than predicted in the subclinical AF trials. And that is what we saw in SINGLE AF.
Thus far, it sounds like I am making a case for no anticoagulation. But it is not that simple. Consider two patients who could have been (and likely were) in SINGLE AF.
A 50-year-old with hypertension and short-duration infrequent AF on her smartwatch. This patient could do well on or off AC.
A 64-year-old person (soon to be 65 years, a cutoff for another risk factor) with insulin-dependent diabetes and persistent AF would likely have a slightly higher stroke risk and would benefit from oral anticoagulation.
If you like algorithms, SINGLE AF is terrible news. Guideline writers will be unable to put the trial’s results into those simple colored boxes telling doctors what to do.
If you value the role of a thinking doctor, you love SINGLE AF. Because now we have to think about the specifics of our patients (eg. duration of AF) and learn their preferences. As I have written here often, maximizers will want to do everything to prevent stroke. For those people, OAC is the obvious answer. Minimizers will look at a 4 in a thousand risk reduction and think it unworthy of taking a daily pill for years.
SINGLE AF allows for both of those translations. And I really like that.
To be honest, much of modern cardiology is going this way. New therapies increasingly have small incremental benefits for which rational people feel differently about.
The final thing to say is that things change over time. We now know that lifestyle measures, such as weight loss, physical fitness and alcohol reduction can eliminate AF. If this happens in the months to years going forward, then the anticoagulation decision becomes easier: no anticoagulation.
Two year f/u is too short. In real practice decades of life must be protected. A 60-70 y.o. must be protected to age 80-90 (or longer). Extrapolate that low percentage of mostly minor strokes to 10-15 times as long as 2 years and the total number of strokes is not so low and the not so minor events are not so rare.
Further, my intuition is that the cumulative stroke incidence over time will be non linear, will accelerate. My reasoning is that new clot will build and grow on older mural clot, gaining thickness while both losing mechanical strength and protruding deeper into the flow of atrial blood.
I remember atrial fib patients with embolic stroke and embolic MI. When warfarin anticoagulation was became recommended for patients with atrial fibrillation I'd already been in clinical medicine more that 20 years and in private practice for 17. The ordeal of warfarin: chasing protimes with dose adjustments, overshoot bruising and bleeding and the thromboembolic events due to inadequate dosing, were significant vs. the dosing simplicity and the efficacy we now enjoy with direct acting oral medications. Let me pass this on to the current generation of physicians and urge that we don't regress based on a short 24 month study.
I’m curious why the AF community doesn’t switch to “CHADSVA” instead of “CHADSVASc”. The “Sc” attributes an extra point to females. Yet that extra point is disregarded at the time of clinical decision. As in this trial, low risk was 1 in males and 2 in females. So being female did not alter risk stratification in any event.
My other clinical conundrum is with newly turned 65 year olds who scored zero previously. They turn 65….happy birthday…here’s a DOAC…go ahead open it! I realize this is the case with any situation that turns a continuous variable into a (false) dichotomy, but few others involve an inexorable march in one direction. And I’ve had multiple pts (they always seem to be engineers) who balk at this “logic”: “doc, yesterday I was fine but today I’m not? That makes no sense”. For these pts, I’ve actually used a biomarker ABC score from Uppsala University (validated in a Swedish population) that treats age as a continuous variable and adds biomarkers (hsTrop and NT BNP). I’m curious how others have handled this type of scenario.